- English
- عربي / Arabic
- മലയാളം / Malayalam

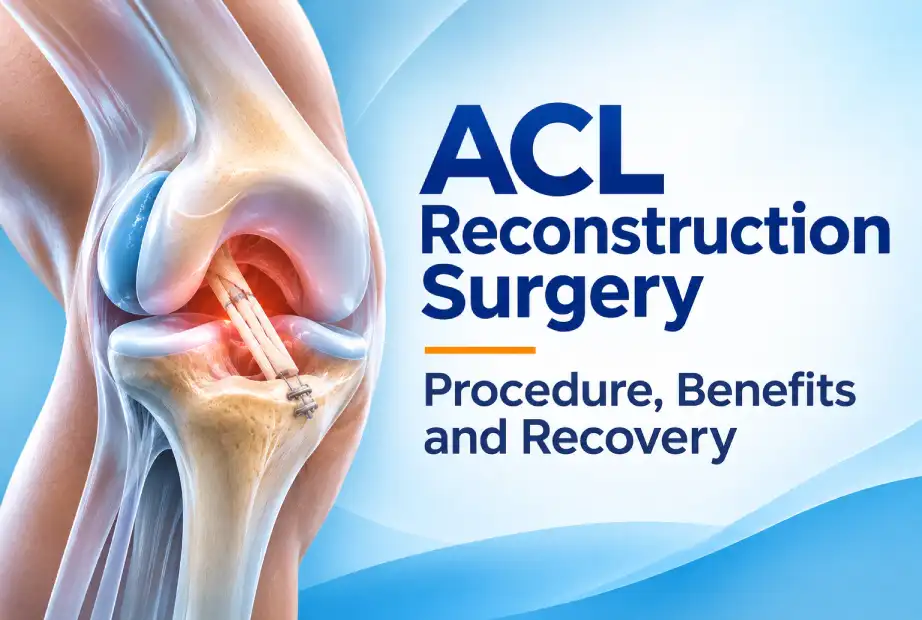
ACL reconstruction surgery replaces a torn anterior cruciate ligament with a tissue graft to help restore knee stability. The ACL is one of the ligaments that controls movement inside the knee, especially during turning and pivoting. An injury can leave the joint feeling unreliable even after the early pain settles. Surgery is considered when instability affects daily life or the activities you want to return to. It is followed by rehabilitation over months.
No. ACL tear treatment can begin with rehabilitation that restores movement, strength, and control. Some people function well without reconstruction, particularly if their knee becomes stable enough for everyday activities and they can adapt higher-risk sports.
Surgery is more likely to be discussed when the knee repeatedly gives way, when returning to pivoting sport is important, or when there are associated injuries that influence the plan. Age alone does not make the decision. Activity demands, knee examination, other health conditions, and willingness to complete rehabilitation all matter.
Ask what continuing rehabilitation without surgery would involve and what findings would prompt reconsideration. This makes the choice more specific than deciding from an MRI report alone.
The specialist examines knee stability, swelling, movement, and muscle strength. MRI can help assess the ACL and identify meniscus or cartilage damage. X-rays may be needed to assess bones or associated injury.
Always describe how the injury happened and whether the knee has given way since. Tell the doctor about work demands, sport, and the movements you cannot trust. A football player, a person with a physical job, and someone focused on comfortable walking may have different priorities.
Before surgery, physiotherapy often aims to reduce swelling and restore movement and muscle control. Starting with a stiff, swollen knee can make recovery harder, although timing also depends on associated injuries.
The surgeon usually replaces the torn ligament using a tendon graft. Options can include tissue from your hamstring, patellar tendon, or quadriceps tendon. Donor tissue is used in selected circumstances. Each choice has potential benefits and trade-offs. Recently synthetic ligament are also available in the market. Donor site morbidity is absent with synthetic ligament
The graft source may affect early discomfort, strength recovery, and particular activities such as kneeling. Age, sport, previous operations, and the surgeon's assessment influence the recommendation. Ask why one graft is preferred for your situation and what that means for rehabilitation.
A reconstruction is different from simply stitching the torn ligament together. Selected repair techniques exist, but they are not suitable for every injury and should not be assumed to offer the same treatment.
The anaesthesia team explains how you will be kept comfortable and asleep or numb for the operation. The surgeon commonly uses arthroscopy, which introduces a camera through small incisions to view the knee.
The graft is passed through prepared tunnels in the thighbone and shinbone and secured with fixation devices. The surgeon checks its position, tension, and the movement of the joint. Associated meniscus damage may be treated during the same operation when appropriate.
If a meniscus repair or another procedure is performed, it may change how much weight you can put on the leg and how far you can bend initially. Ask for instructions that reflect the full operation, rather than a generic ACL programme.
The main aim of knee ligament surgery is improved stability. This can support a return to activities that require turning or changing direction. It does not guarantee a pain-free knee, prevent all future arthritis, or remove the possibility of another injury.
Risks include infection, bleeding, blood clots, stiffness, ongoing pain, and persistent instability. The graft can stretch or tear, and further surgery may be needed. There can also be discomfort or weakness around the area from which a tendon was taken.
Discuss your individual risk and how the team reduces it. Rehabilitation is part of the treatment, not an optional extra after the operation has succeeded.
A single percentage cannot describe every useful outcome. Studies may measure knee stability, patient satisfaction, return to any sport, or return to the previous competitive level. Those are different endpoints, and their rates are not interchangeable.
Many patients achieve better stability after reconstruction, but returning to high-demand sport is less predictable than returning to daily activities. Associated cartilage damage, recurrent injury, rehabilitation, and confidence influence the result. Ask your surgeon which outcome they mean when discussing success and whether their estimate applies to patients like you.
It is also reasonable to ask about re-injury and further surgery separately. Ask whether a quoted percentage describes patients with similar injuries and activity goals, and what period of follow-up it covers.
Pain and swelling are expected initially. You may use crutches and, in some cases, a brace. Follow the specific weight-bearing and exercise instructions from your team. Short, advised walks and prescribed clot-prevention measures help reduce risks.
Early physiotherapy usually focuses on movement, muscle activation, and controlling swelling. Attend wound review and follow instructions about dressings and bathing. Increasing pain, spreading redness, fever, or wound discharge needs prompt advice.
Calf swelling or pain can indicate a clot. Sudden breathlessness or chest pain requires emergency care. Do not wait for the next physiotherapy session to report these symptoms.
ACL reconstruction recovery progresses through stages. Strength, balance, movement quality, and confidence develop gradually. Later exercises may include running, jumping, and sport-specific drills when the knee meets the required criteria.
Return to pivoting sport often takes around nine to twelve months or longer, depending on the patient and assessment. The calendar alone is not clearance. Your team considers strength, functional testing, swelling, and control before recommending higher-demand activity.
Work and driving timelines differ. A desk role may be possible well before heavy manual work or competitive sport. Ask about your actual duties, the operated leg, and whether pain medicines affect safe driving.
If fear of another injury remains after strength improves, discuss it during rehabilitation. Confidence is part of returning safely, and it may improve through supervised progression rather than a sudden return to competition. Agree on the tests and practical milestones you need to meet before each new stage.
ACL surgery cost depends on the graft, fixation devices, associated procedures, anaesthesia, hospital stay, and other care needs. Ask whether the estimate includes scans, physiotherapy, a brace if required, medicines, and follow-up. Rehabilitation costs deserve a place in your budget.
Insurance approval should be checked for the exact procedure and hospital. A package for reconstruction alone may not include treatment of additional injuries discovered or addressed during surgery.
At Baby Memorial Hospital, ACL injuries are assessed by the orthopaedic team with attention to knee stability, associated meniscus or cartilage injuries, activity level and the patient’s goals. When reconstruction is appropriate, arthroscopic techniques are used to reconstruct the ligament and address associated knee injuries when required.
Recovery is planned as part of the treatment from the beginning. Physiotherapy and rehabilitation focus on restoring movement, controlling swelling, rebuilding muscle strength and gradually improving balance and knee control. Follow-up helps the team assess progress before running, jumping, sports or physically demanding work are reintroduced.
The goal at BMH is not simply to reconstruct the ACL. It is to help the knee regain the stability, strength and confidence needed for a safe return to everyday activities and, where appropriate, sport.
FAQs
1. Does every ACL tear require reconstruction surgery?
No. Some patients can regain sufficient knee stability with physiotherapy and activity modification. Surgery is more commonly considered when instability continues, associated injuries are present or the patient wants to return to activities involving frequent turning and pivoting.
2. How long does ACL reconstruction recovery take?
Basic daily activities return much earlier than high-demand sport. Rehabilitation continues for several months and return to pivoting sports often takes around 9–12 months or longer depending on strength, knee control and functional testing.
3. Which graft is used for ACL reconstruction?
Common options include hamstring, patellar tendon and quadriceps tendon peroneus longus grafts. The choice depends on factors such as age, activity level, sport, previous surgery and the individual knee.
4. Can an ACL tear again after reconstruction?
Yes. A reconstructed ACL can be injured again, and the other knee can also sustain an ACL injury. Progressive rehabilitation and appropriate return-to-sport testing help reduce re-injury risk.
5. When can I return to sports after ACL surgery?
Return should be based on recovery milestones rather than time alone. The orthopaedic and rehabilitation team may assess strength, balance, movement control, swelling and sport-specific function before clearing a patient for higher-demand activity.