- English
- عربي / Arabic
- മലയാളം / Malayalam

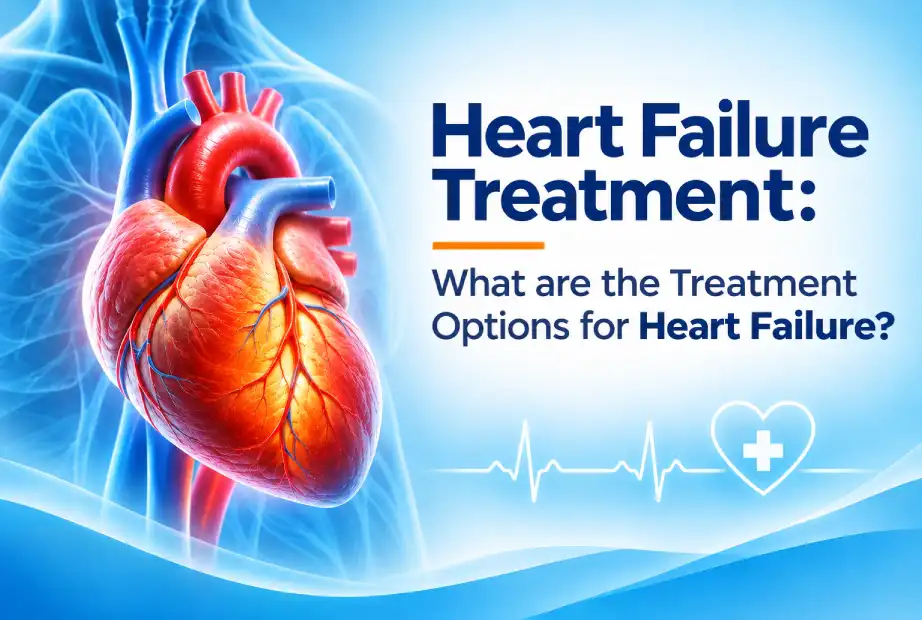
Heart failure means the heart is not filling or pumping well enough to meet the body's needs. It does not mean that the heart has stopped. Some people develop symptoms gradually; others first need care during a sudden episode of breathlessness or fluid build-up. Heart failure treatment aims to ease symptoms, reduce hospital admissions, and improve long-term outcomes where possible. The plan depends on the type of heart failure, its cause, and your other health conditions.
Medicines, follow-up, and daily monitoring often work together. Understanding their roles makes a long-term plan easier to manage.
Common heart failure symptoms include breathlessness, tiredness, reduced exercise tolerance, and swelling around the ankles or legs. You may find it harder to lie flat, need more pillows, or wake during the night feeling short of breath. Fluid retention can also cause a relatively quick increase in body weight.
These symptoms are not unique to heart failure. Lung disease, anaemia, kidney problems, and other conditions can look similar. A medical assessment is needed rather than diagnosing the cause from swelling or tiredness alone.
Seek emergency care for severe breathlessness at rest, chest pain, fainting, blue or grey lips, or a sudden major deterioration. Do not wait for a routine review or try to manage a severe episode by taking extra tablets without a plan.
Possible causes include coronary artery disease, previous heart attack, longstanding high blood pressure, valve disease, and disorders of the heart muscle. Abnormal rhythms and other illnesses can contribute or make symptoms worse.
Identifying the cause is important because some problems need specific treatment. A damaged valve may need intervention, while a rhythm disturbance may require its own management. Sometimes several factors are involved.
Tell the doctor about alcohol use, previous cancer treatment, family history, and all medicines or supplements. This is not about assigning blame. It helps the team identify reversible contributors and avoid treatments that could worsen the condition.
The assessment usually includes your history and examination, an ECG, and blood tests. A blood marker such as BNP or NT-proBNP may help guide the evaluation. An echocardiogram uses ultrasound to assess the heart's pumping, filling, and valves.
One measurement, called ejection fraction, describes the proportion of blood pumped out of the main chamber with each beat. Heart failure can occur with a reduced ejection fraction or with a preserved one. A preserved percentage does not mean symptoms should be dismissed.
Additional tests depend on the suspected cause. Ask which type you have and what the findings mean for treatment, rather than focusing on a single number without context.
For many people with reduced ejection fraction, treatment includes several groups of medicines that work in different ways. These commonly include an ARNI, ACE inhibitor or ARB; a suitable beta blocker; a mineralocorticoid receptor antagonist; and an SGLT2 inhibitor. Your clinician chooses the combination and doses according to blood pressure, kidney function, potassium, and other factors.
Some of these medicines were first associated with diabetes or blood pressure treatment, but can have a role in heart failure even without those conditions. Not every medicine is appropriate for every person.
The plan for preserved ejection fraction also includes treatment of contributing conditions and, in suitable patients, medicines such as SGLT2 inhibitors. Your heart failure medication should reflect your diagnosis rather than another patient's prescription.
Diuretics, sometimes called water tablets, help the body remove excess salt and water. They can reduce ankle swelling and breathlessness caused by congestion. Congestive heart failure treatment often includes them when fluid retention is present.
The dose may change as symptoms and fluid levels change. Blood tests are important because kidney function and electrolytes can be affected. Frequent urination after a dose is expected, but marked dizziness, weakness, or reduced urine output should be discussed.
Do not adjust the dose unless your team has given you a clear written plan. If a flexible plan is appropriate, ask exactly which weight or symptom changes should trigger it and when you must call instead.
Some patients need treatment for coronary disease or a damaged valve. Others may benefit from a device. An implantable defibrillator can reduce the risk from certain dangerous rhythms in selected patients. Cardiac resynchronisation therapy helps selected hearts beat in a more coordinated way.
Eligibility depends on measurements, symptoms, rhythm, electrical patterns, and response to medicines. A device is not a replacement for ongoing treatment. In advanced disease, specialist teams may discuss mechanical circulatory support, transplantation, or care focused on comfort and quality of life.
Ask what a proposed intervention is intended to improve and what care it will require afterwards.
Weight monitoring can help identify fluid retention before symptoms become severe. If your team recommends it, weigh yourself under similar conditions and record the result. Ask for a personal threshold for contacting the service; a meaningful change should be interpreted alongside symptoms.
Notice whether breathing, swelling, appetite, or usual walking distance is changing. Keep a current medicine list and bring it to appointments. A simple record is often more useful than trying to remember several weeks of changes during a brief consultation.
If symptoms worsen, contact the team promptly. Waiting until breathing becomes very difficult can make treatment more complicated.
Heart failure management usually includes advice about salt intake and an eating pattern suited to your overall health. Very salty packaged foods can make fluid control harder. A dietitian can help adapt familiar meals rather than leave you with broad instructions that are difficult to use.
Fluid restriction is not the same for everyone. Some patients need a limit; others do not. Ask for a specific daily allowance if one is recommended, including what counts towards it.
Check before using salt substitutes, because some contain potassium. Also ask before taking non-prescription painkillers or supplements. Certain anti-inflammatory medicines can worsen fluid retention or kidney function.
Tell the team if low mood, anxiety, or poor sleep is making the plan harder to follow. These concerns deserve care too. A relative can help with appointments and records, but the arrangements should respect your preferences and the level of support you want.
Appropriate activity can improve strength and confidence when your condition is stable. Cardiac rehabilitation offers supervised exercise and education for eligible patients. The starting level should match your symptoms and recent clinical course.
Follow-up visits review symptoms, blood pressure, blood tests, and medicines. Doses may be increased gradually if tolerated. Tell the team about side effects or difficulty obtaining medicines so the plan can be adjusted realistically.
At Baby Memorial Hospital, heart failure care is managed through the cardiology team with assessment of heart function, symptoms and the underlying cause. Care may include medicines, ECG and echocardiography, management of fluid build-up, and device-based or interventional treatment when clinically appropriate.
Follow-up is an important part of heart failure management at BMH. The team monitors symptoms, blood pressure, kidney function and medicines, while cardiac rehabilitation and lifestyle guidance can support suitable patients in returning to activity safely. The aim is to keep symptoms controlled, reduce avoidable hospital admissions and recognise worsening heart failure early.
Living with heart failure involves continuing care, but the plan should be understandable. Before leaving a visit, make sure you know what each medicine is for, which changes require a call, and when your next blood test or review is due.
1. Can heart failure be treated successfully?
Heart failure is often a long-term condition, but appropriate medicines, treatment of the underlying cause and regular follow-up can improve symptoms and reduce the risk of hospitalisation. The outlook varies according to the type and severity of heart failure.
2. What are the early warning signs of heart failure?
Increasing breathlessness, unusual tiredness, reduced exercise tolerance, ankle or leg swelling and difficulty lying flat can be warning signs. A rapid increase in weight may also indicate fluid retention.
3. What tests are used to diagnose heart failure?
Assessment may include an ECG, echocardiogram, blood tests and tests such as BNP or NT-proBNP. Further investigations may be recommended to identify the underlying cause.
4. Can people with heart failure exercise?
Many people with stable heart failure benefit from suitable physical activity. The amount and type should be based on individual symptoms and medical advice. Cardiac rehabilitation may provide supervised exercise for eligible patients.
5. When should someone with heart failure seek emergency care?
Severe breathlessness at rest, chest pain, fainting, blue or grey lips, confusion or a sudden major worsening of symptoms requires urgent medical attention.